
Журнал "Гастроэнтерология" Том 60, №3, 2026
Вернуться к номеру
Гастроезофагеальна рефлюксна хвороба у пацієнтів з ожирінням: моторні, імунометаболічні та мукозально-бар’єрні механізми прогресування. Частина 2
Авторы: Шевцова О.М.
ДУ «Інститут гастроентерології НАМН України», м. Дніпро, Україна
Рубрики: Гастроэнтерология
Разделы: Справочник специалиста
Версия для печати
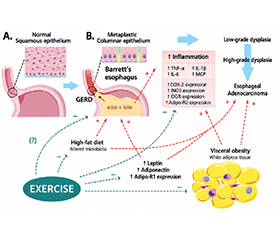
Гастроезофагеальна рефлюксна хвороба (ГЕРХ) у пацієнтів з ожирінням формується не лише внаслідок підвищення внутрішньочеревного тиску, а й через складну взаємодію моторних, імунометаболічних, гормональних і мукозально-бар’єрних порушень. Мета роботи: узагальнити сучасні дані щодо патомеханізмів прогресування ГЕРХ у пацієнтів з ожирінням з акцентом на механічні та моторні чинники, цитокіново-гормональний дисбаланс, ушкодження слизового бар’єра стравоходу та клітинні мішені при різних метаболічних фенотипах. Матеріал підготовлено у форматі літературного огляду з елементами систематизованого пошуку в базах PubMed/Medline, Scopus, Web of Science, ScienceDirect та Cochrane Library. До аналізу включалися клінічні, когортні, інструментальні, оглядові та метааналітичні дослідження, у яких оцінювалися зв’язки між ожирінням, метаболічною дисфункцією, моторикою стравоходу, кислотною експозицією, цитокінами, адипокінами, гормональними регуляторами та структурною цілісністю слизової оболонки стравоходу. Узагальнені дані свідчать, що при метаболічно нездоровому ожирінні та метаболічно нездоровій нормальній масі тіла провідними механізмами є інсулінорезистентність, дисбаланс лептину й адипонектину, активація TNF-α, IL-6, IL-1β, зниження протизапальної регуляції, порушення тонусу нижнього стравохідного сфінктера, збільшення частоти транзиторних релаксацій, зниження стравохідного кліренсу, порушення функції щільних контактів епітелію. Вісцеральна жирова тканина виступає активним ендокринним та імунометаболічним органом, що поєднує системне запалення з локальним пошкодженням слизової оболонки. Отримані дані обґрунтовують необхідність патогенетично орієнтованого підходу до діагностики, прогнозування рефрактерності та профілактики ускладнень ГЕРХ у пацієнтів з ожирінням.
Gastroesophageal reflux disease (GERD) in patients with obesity develops not only due to increased intra-abdominal pressure but also through a complex interaction of motor, immunometabolic, hormonal and mucosal barrier disturbances. The aim of this review was to summarize current evidence on the mechanisms of GERD progression in obese patients, focusing on mechanical and motor factors, cytokine and hormonal imbalance, impairment of the esophageal mucosal barrier and cellular targets in different metabolic obesity phenotypes. The article was prepared as a literature review with elements of a systematic search in PubMed/MEDLINE, Scopus, Web of Science, ScienceDirect and Cochrane Library. Clinical, cohort, instrumental, review and meta-analytic studies evaluating the relationships between obesity, metabolic dysfunction, esophageal motility, acid exposure, cytokines, adipokines, hormonal regulators and structural integrity of the esophageal mucosa were included. Current evidence indicates that in metabolically unhealthy obesity and metabolically unhealthy normal weight, the leading mechanisms include insulin resistance, leptin and adiponectin imbalance, activation of tumor necrosis factor α, interleukins and 1β, reduced anti-inflammatory regulation, impaired lower esophageal sphincter tone, increased transient lower esophageal sphincter relaxations, reduced esophageal clearance and disruption of epithelial tight junctions. Visceral adipose tissue acts as an active endocrine and immunometabolic organ linking systemic inflammation with local mucosal injury. These findings support a pathogenetically oriented approach to diagnosis, prediction of treatment refractoriness and prevention of GERD complications in obese patients.
гастроезофагеальна рефлюксна хвороба; ожиріння; моторика стравоходу; нижній стравохідний сфінктер; цитокіни; адипокіни; інсулінорезистентність; слизовий бар’єр; стравохід Барретта
gastroesophageal reflux disease; obesity; esophageal motility; lower esophageal sphincter; cytokines; adipokines; insulin resistance; mucosal barrier; Barrett’s esophagus
Для ознакомления с полным содержанием статьи необходимо оформить подписку на журнал.
- Bertin L. et al. Pathophysiology of Gastroesophageal Reflux Disease. Digestion. 2025. P. 1-17. doi: 10.1159/000547023.
- Xie M., Deng L., Fass R., Song G. Obesity is associated with higher prevalence of gastroesophageal reflux disease and reflux related complications: A global healthcare database study. Neurogastroenterol Motil. 2024. Vol. 36(4). P. e14750. doi: 10.1111/nmo.14750.
- García Ruiz de Gordejuela A., Ibarzabal Olano A., Petrola Chacón C.G., González López Ó. Obesity related pathophysiological aspects favouring Gastroesophageal Reflux Disease. Cir Esp (Engl Ed). 2023. Vol. 101(Suppl 4). P. S3-S7. doi: 10.1016/j.cireng.2022.12.007.
- Masood M., Low D., Deal S.B., Kozarek R.A. Gastroesopha–geal Reflux Disease in Obesity: Bariatric Surgery as Both the Cause and the Cure in the Morbidly Obese Population. J Clin Med. 2023. Vol. 12(17). P. 5543. doi: 10.3390/jcm12175543.
- Alimi Y., Azagury D.E. Gastroesophageal Reflux Disease and the Patient with Obesity. Gastroenterol Clin North Am. 2021. Vol. 50(4). P. 859-870. doi: 10.1016/j.gtc.2021.08.010.
- Griadil T.I., Bezushko B.V., Dutko O.O., Lopit M.M. The clini–cal and pathogenetic manifestations of gastroesophageal reflux disease and obesity and approaches to their diagnosis, treatment, and prevention: current state of the problem (literature review). Wiad Lek. 2025. Vol. 78(4). P. 937-942. doi: 10.36740/WLek/203909.
- Page M.J. et al. PRISMA 2020 explanation and elaboration: updated guidance and exemplars for reporting systematic reviews. BMJ. 2021. Vol. 372. P. n160. doi: 10.1136/bmj.n160.
- He T. et al. Association Between Different Metabolic Obesity Phenotypes and Erosive Esophagitis: A Retrospective Study. Diabetes Metab Syndr Obes. 2024. Vol. 17. P. 3029-3041. doi: 10.2147/DMSO.S471499.
- He T. et al. Relationship of different metabolic obesity phenotypes with reflux esophagitis: a propensity score matching analysis. BMC Endocr Disord. 2024. Vol. 24(1). P. 239. doi: 10.1186/s12902-024-01771-6.
- He T., Zhang M., Tong M., Duan Z. Comparison of Esophageal Dysmotility and Reflux Burden in Patients with Different Metabo–lic Obesity Phenotypes Based on High-Resolution Impedance Manometry and 24-h Impedance-pH. Obes Facts. 2024. Vol. 17(6). P. 629-640. doi: 10.1159/000541130.
- He T. et al. Associations of Metabolically Healthy Obesity with Gastroesophageal Reflux Disease and Ineffective Esophageal Motility. Turk J Gastroenterol. 2025. Vol. 36(6). P. 371-380. doi: 10.5152/tjg.2025.24351.
- Опарін А.Г. та ін. Патофізіологічні та біохімічно-молекулярні концепції коморбідного перебігу гастроезофагеальної рефлюксної хвороби та ожиріння в осіб молодого віку. Східно–європейський журнал внутрішньої та сімейної медицини. 2024. № 2. С. 70-80. doi: 10.15407/internalmed2024.02.070.
- Stepanov Y. et al. Effects of visceral obesity on cytokine and hormonal regulation in patients with gastroesophageal reflux disease. Gastroenterology. 2023. Vol. 57(3). P. 135-140. doi: 10.22141/2308-2097.57.3.2023.551.
- Mosiychuk L., Shevtsova O., Tatarchuk O., Petishko O. Characteristics of metabolic syndrome in the servicemen with erosive esophagitis in wartime conditions. Gastroenterology. 2024. Vol. 58(4). P. 234-239. doi: 10.22141/2308-2097.58.4.2024.633.
- Fu S. et al. Metabolic syndrome is associated with higher rate of gastroesophageal reflux disease: a meta-analysis. Neurogastroenterol Motil. 2022. Vol. 34(5). P. e14234. doi: 10.1111/nmo.14234.
- Hsu W.H. et al. Metabolic syndrome is associated with gastroesophageal reflux disease in a large Taiwanese population study. Int J Med Sci. 2025. Vol. 22(7). P. 1555-1561. doi: 10.7150/ijms.109616.
- He T. et al. Association between gastroesophageal reflux di–sease and metabolic syndrome: a bidirectional two-sample Mendelian randomization analysis. Arch Med Sci. 2024. Vol. 20(5). P. 1715-1719. doi: 10.5114/aoms/193708.
- Leng X., Liao W.Z., Zheng F.P. Gastroesophageal reflux di–sease and non-alcoholic fatty liver disease: a two-sample Mendelian randomization combined with meta-analysis. Sci Rep. 2024. Vol. 14(1). P. 12633. doi: 10.1038/s41598-024-63646-z.
- Mikolasevic I. et al. Association between Gastroesophageal Reflux Disease and Elastographic Parameters of Liver Steatosis and Fibrosis: Controlled Attenuation Parameter and Liver Stiffness Measurements. Can J Gastroenterol Hepatol. 2021. Vol. 2021. P. 6670065. doi: 10.1155/2021/6670065.
- Khosravifar M., Rezaei M., Heydari R. Association of Gastroesophageal Reflux Disease Symptoms and Non-alcoholic Fatty Liver Disease by Eliminating the Body Mass Index Effect. Govaresh. 2021. Vol. 26(2). P. 108-112.
- Yuan S., Larsson S.C. Adiposity, diabetes, lifestyle factors and risk of gastroesophageal reflux disease: a Mendelian randomization study. Eur J Epidemiol. 2022. Vol. 37(7). P. 747-754. doi: 10.1007/s10654-022-00842-z.
- Budiyani L., Purnamasari D., Simadibrata M., Abdullah M. Insulin Resistance in Gastroesophageal Reflux Disease. Acta Med Indones. 2018. Vol. 50(4). P. 336-342. PMID: 30631000.
- Budiyani L., Purnamasari D., Simadibrata M., Abdullah M. Differences in the Insulin Resistance Levels Measured by HOMA-IR between Patients with Erosive and Non-Erosive Gastroesophageal Reflux Disease. J ASEAN Fed Endocr Soc. 2017. Vol. 32(2). P. 139-144. doi: 10.15605/jafes.032.02.07.
- Paris S. et al. Obesity and its effects on the esophageal mucosal barrier. Am J Physiol Gastrointest Liver Physiol. 2021. Vol. 321(3). P. G335-G343. doi: 10.1152/ajpgi.00199.2021.
- Bilski J. et al. Role of Obesity, Physical Exercise, Adipose Tissue-Skeletal Muscle Crosstalk and Molecular Advances in Barrett’s Esophagus and Esophageal Adenocarcinoma. Int J Mol Sci. 2022. Vol. 23(7). P. 3942. doi: 10.3390/ijms23073942.
- Ribolsi M., Guarino M.P.L., Tullio A., Cicala M. Post-reflux swallow-induced peristaltic wave index and mean nocturnal baseline impedance predict PPI response in GERD patients with extra esopha–geal symptoms. Dig Liver Dis. 2020. Vol. 52(2). P. 173-177. doi: 10.1016/j.dld.2019.09.011.
- Prajapati S.K., Senthamizhselvan K., Murugesan R., Mohan P. Spectrum of esophageal manometry and 24-h pH impedance findings in non-erosive gastroesophageal reflux disease and response to phenotype-based treatment-A prospective observational study. Indian J Gastroenterol. 2025. Vol. 44(1). P. 64-71. doi: 10.1007/s12664-024-01659-2.
- Lu W., Li X., Luo Y. FGF21 in obesity and cancer: New insights. Cancer Lett. 2021. Vol. 499. P. 5-13. doi: 10.1016/j.canlet.2020.11.026.
- Stepanov Y. et al. The role of fibroblast growth factor 21 in metabolic processes in patients with gastrointestinal diseases. Gastroenterology. 2024. Vol. 58(2). P. 87-92. doi: 10.22141/2308-2097.58.2.2024.600.
- He M. et al. Association Between Psychosocial Disorders and Gastroesophageal Reflux Disease: A Systematic Review and Meta-analysis. J Neurogastroenterol Motil. 2022. Vol. 28(2). P. 212-221. doi: 10.5056/jnm21044.
- Chandran S. et al. The Inclusion of Voice Assessments to Aid Diagnostic and Surgical Decision Making for Patients With Laryngopharyngeal Reflux. J Voice. 2022. P. S0892-1997(22)00082-0. doi: 10.1016/j.jvoice.2022.03.016.